Diabetes
More than 80 percent improve or resolve
Blood sugar often improves within days of surgery, before meaningful weight loss, because the rerouting changes gut hormones immediately. Many patients go home on far less medication.
Call Us Today
216-377-7257 [email protected]Lyndhurst
5035 Mayfield Rd, Suite 100Westlake
25200 Center Ridge Rd, Suite 1100Roux-en-Y gastric bypass has been performed and studied longer than any modern weight loss operation. It remains the strongest tool available for patients with type 2 diabetes and severe acid reflux, and Dr. Linden Karas performs it for patients across Cleveland and Northeast Ohio.

What It Is
In a Roux-en-Y gastric bypass, Dr. Karas divides the top of the stomach to create a pouch about the size of an egg, holding around an ounce. She then brings up a section of small intestine and connects it directly to that pouch. Food travels from the pouch straight into the intestine, bypassing the rest of the stomach and the first portion of the small bowel. Drawn on paper, the reconnected intestine forms a Y, which is where the name comes from.
The bypass works three ways at once. The small pouch restricts how much you can eat. The shortened food path modestly reduces how many calories you absorb. And the rerouting changes gut hormones directly: ghrelin, the hunger hormone, falls, while GLP-1 and PYY, the hormones that signal fullness and regulate blood sugar, rise.
That hormonal shift is why blood sugar in diabetic patients often improves within days of surgery, before any real weight has come off. The same pathway that made GLP-1 medications famous is one the bypass has been switching on for decades.

Who Qualifies
The qualifying criteria mirror the sleeve: a BMI of 40 or higher, a BMI of 35 or higher with a weight-related condition, or under current national guidelines a BMI of 30 or higher with type 2 diabetes or another condition that is not controlled.
Within those criteria, two groups should hear the case for bypass specifically:
Bypass is not for everyone. Patients who need long-term anti-inflammatory medication, have had extensive prior abdominal surgery, or struggle with certain nutritional issues may be better served by the gastric sleeve, and that judgment is what the consultation is for.
The Operation
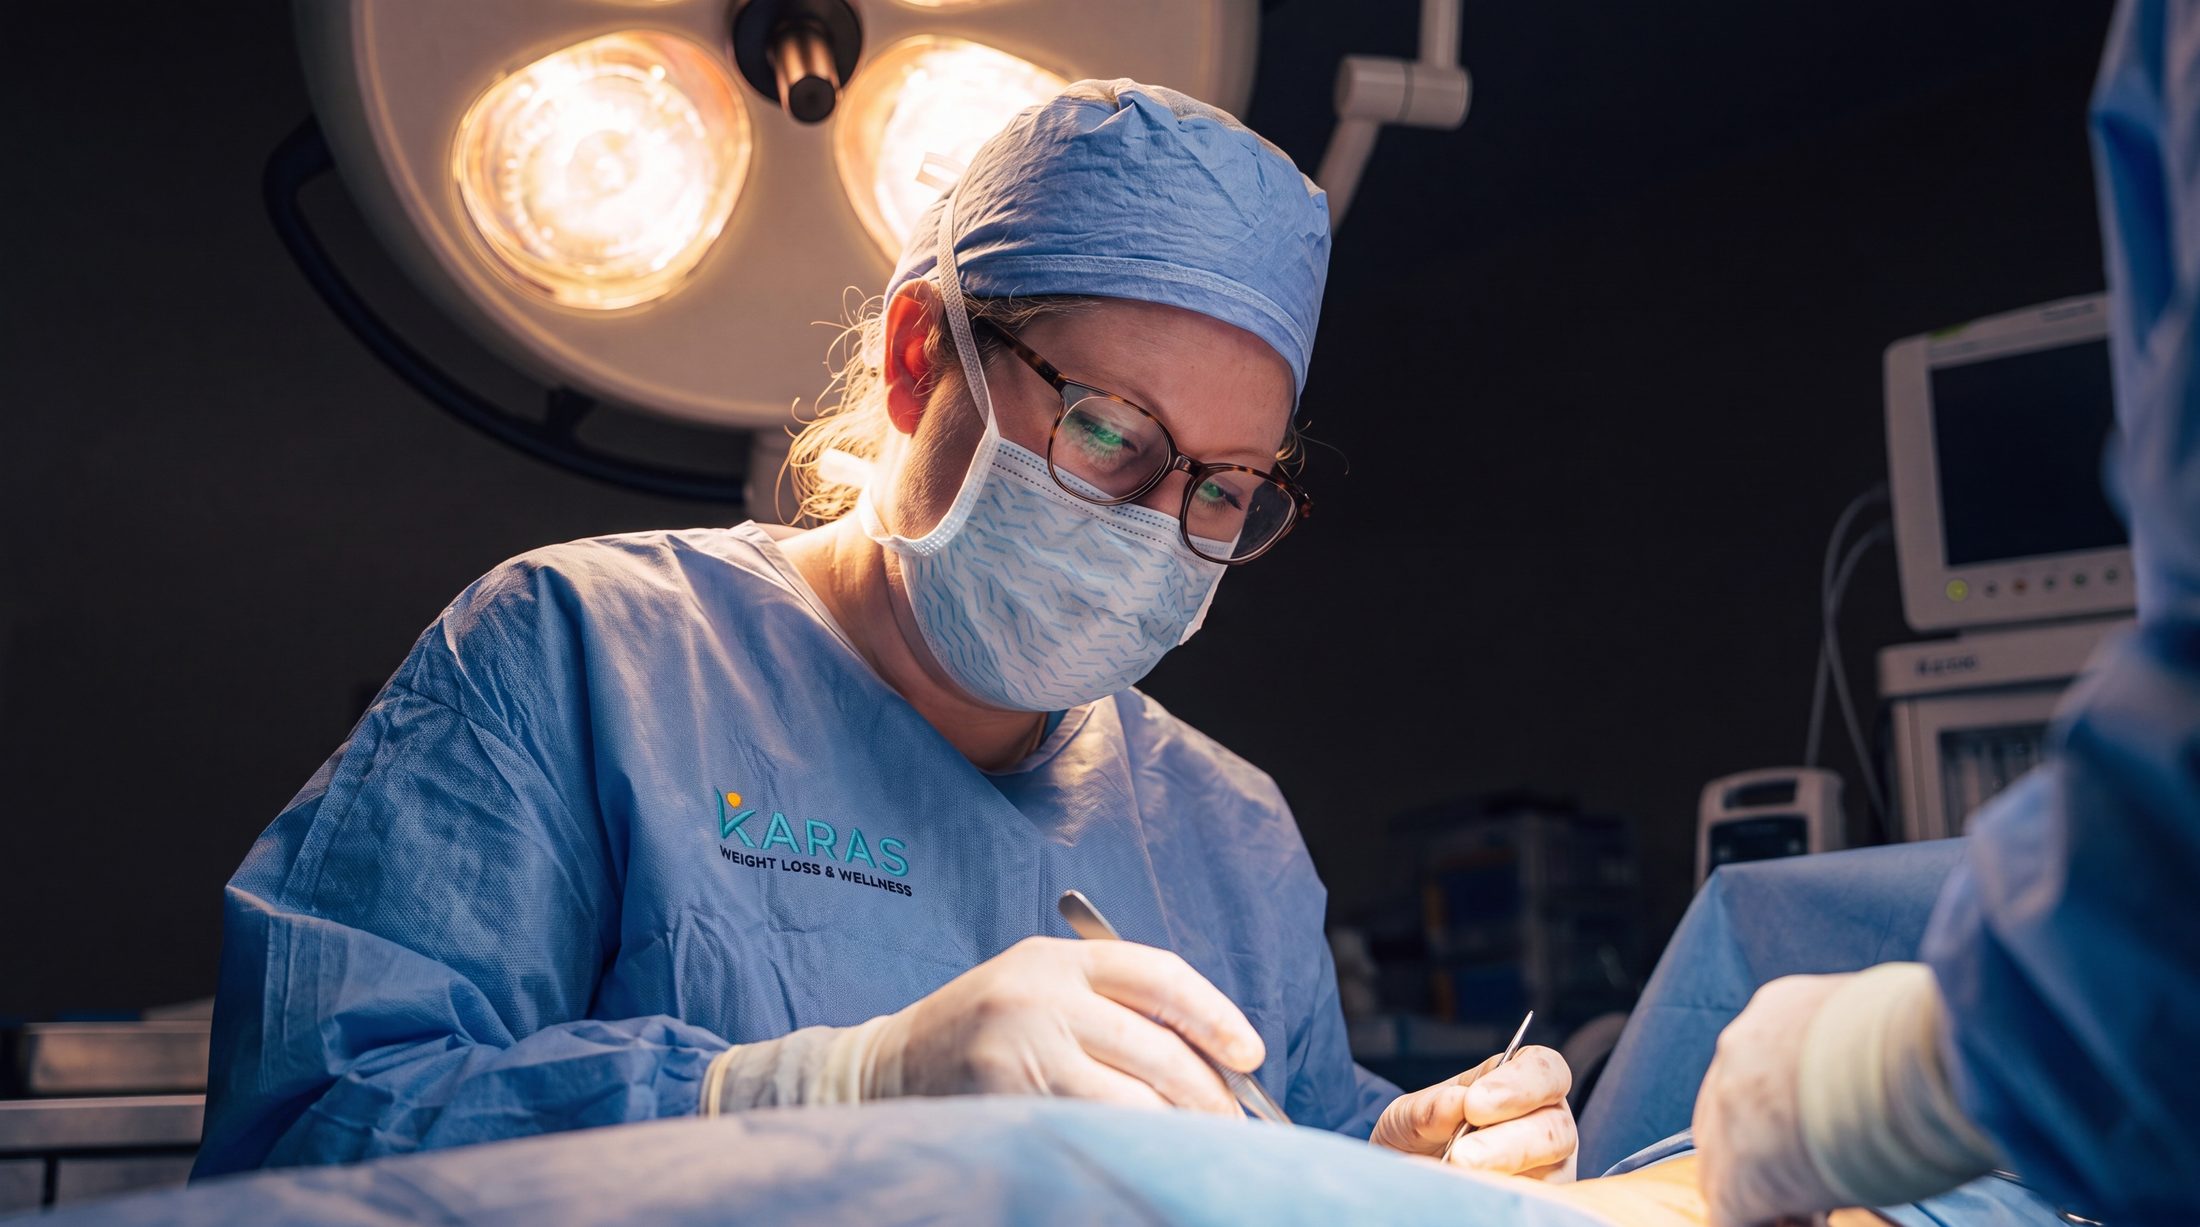
The bypass is performed laparoscopically under general anesthesia through a few small incisions and takes about two hours. Dr. Karas creates the pouch with surgical staplers, divides the small intestine, and builds two connections: intestine to pouch, and intestine to intestine to complete the Y. Both connections are tested before closing.
Bypass patients at the hospital systems typically stay two nights or more. In this practice, qualifying patients have their bypass in an accredited ambulatory surgery center and go home the same day.
Patients who need monitoring stay overnight at UH Geauga Medical Center or Southwest General, where Dr. Karas holds privileges. She will tell you upfront if you are in one of those groups: insulin-dependent patients with hard-to-predict sugars, because insulin needs often drop sharply after bypass, patients on blood thinners, and patients with significant heart disease or home oxygen.
Results
Weight loss runs 60 to 80 percent of excess weight over 18 to 24 months. The disease outcomes are what set bypass apart.
Diabetes
Blood sugar often improves within days of surgery, before meaningful weight loss, because the rerouting changes gut hormones immediately. Many patients go home on far less medication.
Reflux
Bypass is the operation of choice when heartburn is part of your story, and the one revision surgeons turn to when a sleeve has made reflux worse.
Sleep apnea
High blood pressure resolves or improves in more than half of patients, and long-term mortality drops by roughly a third compared with no surgery.
Preparation And Recovery
The workup mirrors the sleeve pathway: consultation with Dr. Karas at the start, usually within a week of calling, then blood work, an EKG, an evaluation of the stomach and esophagus, a nutrition assessment, and a psychological evaluation. Insurance-required supervised diet months are managed and documented by the practice.
Smoking has to stop completely before a bypass, and this one is not negotiable. Nicotine causes ulcers at the new connection. The final two weeks before surgery are a liquid diet to shrink the liver and make the operation safer.
| Timeframe | What you can do | What you are eating |
|---|---|---|
| Days 1 to 7 | Walking within hours of surgery and several times a day after. Fatigue and incision soreness fade over the week. | Clear liquids into full liquids, with protein shakes and fluid sipped steadily through the day. |
| Weeks 2 to 4 | Desk work typically resumes within two weeks. Strenuous activity and lifting stay off the table. | Pureed then soft foods, protein first, in five or six small meals rather than three large ones. |
| Weeks 4 to 6 | Restrictions lift and exercise builds back up. | Soft solids one food at a time, then regular food in small portions by around week six. |
| Month 3 and beyond | Eating has settled into its long-term pattern and energy is typically better than before surgery. | 80 to 100 grams of protein daily, 64 ounces of fluid between meals, bariatric vitamins for life. Concentrated sugar triggers dumping, and ibuprofen is permanently off the table. |
Risks
At experienced centers the risk of death within 30 days of a bypass is about 1 in 1,000, lower than gallbladder surgery and far lower than the lifetime cost of staying at a BMI over 40.
About 2 percent
The complication watched for most closely in the first days, which is why both connections are tested before closing.
A few percent
Narrowing shows up as trouble keeping food down and is fixed with an endoscopic balloon stretch. Ulcers are why nicotine and anti-inflammatories are permanently off limits.
About 3 percent
Intestine slips through a space created by the rerouting and is repaired laparoscopically. Sudden crampy pain long after surgery always deserves a call.
Blood clots occur in about 1 percent. Gallstones are common during rapid weight loss and sometimes lead to gallbladder removal later.
Vitamin deficiency is the bypass’s known long-term weakness, because the bypassed intestine is where iron, calcium, and B12 do much of their absorbing. Iron deficiency shows up in a quarter to half of patients over the years when supplements slip. The defense is boring and completely effective: bariatric vitamins every day for life and lab work on schedule.
Cost And Coverage
Gastric bypass is covered by most insurance plans under the same criteria as the sleeve, and the practice verifies benefits and manages authorization from the first visit.
Self-pay patients get one all-inclusive price known before surgery. The same operation from the same surgeon costs thousands less in a surgery center than in a hospital, because the difference is the building’s facility fee rather than anything about your care. Financing with easy monthly payments is available through CareCredit and Cherry, and checking your options does not affect your credit score.
Financing Available
Financing is available for bariatric surgery, the Allurion balloon, Mag-DI and the medical weight loss program. Apply online in minutes, get a decision fast, and pay in monthly installments instead of all at once. Checking your options does not affect your credit score.
See financing options
Promotional financing on purchases of $200 or more, including no interest if paid in full within the promotional period, plus longer plans with fixed monthly payments on larger amounts. Prequalify online with no effect on your credit score. Accepted at Karas Weight Loss and Wellness.
CareCredit financing details →
Monthly payment plans up to 60 months, with 0% APR for qualifying applicants. Apply in about a minute with a soft credit check that does not affect your score. High approval rates, including for patients who have been turned down for a card before.
Cherry payment plan details →Financing is subject to credit approval. Get your written quote at a consultation and the office will help you set up a monthly payment plan. Read the full financing details.
Compare Your Options
| Gastric bypass | Gastric sleeve | SADI-S | |
|---|---|---|---|
| How it works | Egg-sized pouch plus intestinal rerouting, with a direct change in gut hormones | About 80 percent of the stomach removed, hunger hormone drops | Sleeve plus a single intestinal reroute |
| Typical weight loss | 60 to 80 percent of excess weight | 50 to 70 percent of excess weight | 70 to 85 percent of excess weight |
| Diabetes remission | Highest of the common operations, over 80 percent | More than 75 percent see improvement | Highest overall, some series above 90 percent |
| Effect on reflux | Usually cures it | Can make it worse | Poor choice if reflux is significant |
| Dumping syndrome | Possible with concentrated sugar | No | Rare, the stomach valve is preserved |
| Availability here | Available now | Available now | Coming soon |
Bypass patients who regained weight years ago have their own path, covered on the revision surgery page. Dr. Karas performs all of these herself, including Mag-DI.
Questions
Typically 60 to 80 percent of your excess weight over 18 to 24 months, which is roughly 30 percent of total body weight. Long-term studies show more than 90 percent of patients keep off at least half their excess weight.
Better for two specific situations: significant reflux, which bypass usually cures and a sleeve can worsen, and long-standing type 2 diabetes, where bypass has the highest remission rates. For many other patients the sleeve’s simplicity wins. This is exactly the conversation to have with your surgeon, early.
A rush of nausea, cramping, sweating, and racing heartbeat within about 30 minutes of eating concentrated sugar, caused by sugar entering the intestine too fast. It is avoidable by eating the way the surgery intends, and most patients experience it rarely if at all.
It resolves or improves in more than 80 percent of bypass patients, and blood sugar often improves within days of surgery, before significant weight loss. Patients frequently leave on far less medication than they arrived with. Lasting remission depends on how long you have had diabetes and how well the weight stays off.
About two hours under general anesthesia, done laparoscopically through small incisions.
For qualifying patients, yes. Dr. Karas performs bypass at an accredited ambulatory surgery center with same-day discharge, a model she was the first to bring to Northeast Ohio. Insulin-dependent patients with unstable sugars, patients on blood thinners, and patients with significant heart or lung disease stay overnight at one of her hospital facilities instead.
Technically yes, since nothing is removed, but reversal is a major operation reserved for rare medical situations. Plan as if it is permanent.
Carefully and not soon. The same drink produces a higher, faster peak after bypass, and post-surgical patients carry a real risk of alcohol problems. Wait until your weight is stable and treat your tolerance as reset to zero.
Anti-inflammatory pain relievers such as ibuprofen and naproxen, permanently, because they cause ulcers at the new connection. Nicotine in any form for the same reason.
The pouch or its outlet may have stretched, and that is fixable. The practice evaluates bypass anatomy with an endoscopy and offers revision options, including a planned endoscopic outlet repair called TORe.
Yes, and fertility commonly improves. Wait 12 to 18 months so pregnancy starts after the rapid weight loss phase, and tell your OB about the bypass so your vitamin levels get watched.
Most plans cover it under standard BMI criteria, usually after a documented supervised diet period. The practice checks your exact benefits before anything moves forward, and all-inclusive self-pay pricing is available.
Next Step
You will get all-inclusive pricing, your insurance options, and a consultation with the surgeon who would perform your operation, usually within about a week.
Limited time
One visit with Dr. Karas covers the surgical options and the medical weight loss program with GLP-1 medication management, at the Lyndhurst or Westlake office, at no charge.
Or call 216.377.7257Free consultation
Free for new patients at both the Lyndhurst and Westlake offices.
Thank you. We have your request and someone from the office will follow up shortly.